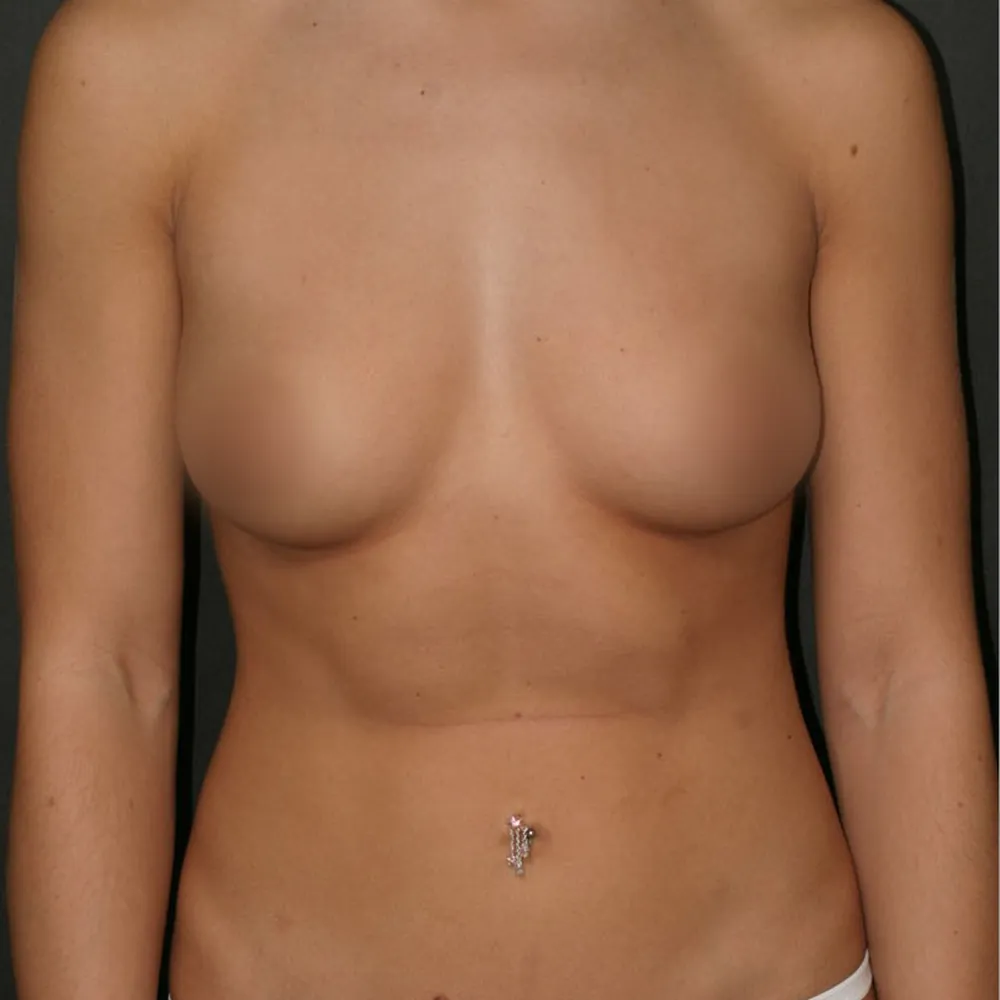
What breast augmentation is
Breast augmentation places an implant behind each breast to increase its volume and shape it. It is usually chosen when the breasts are naturally small, when they have lost volume after pregnancy, breastfeeding or weight loss, or when there is a clear asymmetry between them.
The aim is not a particular cup size but a bust in proportion with the rest of the body. That is why two women who ask for “one size bigger” may need very different implants.
Who it is for
Breast augmentation can be a good option for women who:
- would like fuller or better shaped breasts;
- have lost volume after pregnancy, breastfeeding or weight loss;
- have noticeably asymmetric breasts;
- are healthy, do not smoke or are willing to stop for a while, and have realistic expectations.
If the breasts have also dropped (the nipple sits at or below the fold under the breast), an implant alone will not lift them. In these cases a breast lift is discussed, with or without an implant.
It is better to postpone surgery if you are planning a pregnancy soon, are breastfeeding or your weight is not yet stable.
Choosing the implant
At the consultation the doctor measures your chest and breasts, assesses tissue thickness and skin quality, and then explains the options. The main decisions are:
- Volume, chosen according to chest width and the tissue available, not only the size you would like.
- Shape: round implants give more fullness in the upper part of the breast; anatomical (“teardrop”) implants follow the natural profile more closely. Neither is better in general; the choice depends on the breast we start from.
- Position: the implant can sit in front of the pectoral muscle or partly behind it (the “dual plane” technique). A partly submuscular position covers the implant better in slim women.
- Incision: most often in the fold under the breast, where the scar is hidden; alternatively at the edge of the areola or in the armpit.
Modern implants are made of cohesive silicone gel with a strong shell. You will receive information about the manufacturer, the warranty and the implant serial numbers.
How the operation is done
The operation is done under general anaesthesia given by the anaesthetist and usually takes one to two hours. Through the chosen incision a pocket is created for the implant in the planned position, the implant is inserted, symmetry is checked and the incision is closed, usually with dissolving stitches.
An overnight stay for monitoring is generally recommended, depending on the case.
Preparation
- Blood tests and, depending on age and history, a breast ultrasound or mammogram.
- Stopping smoking at least a few weeks before and after surgery.
- Stopping medication and supplements that increase bleeding risk, with the prescribing doctor’s approval.
- Getting the support bra or binder recommended by the doctor before the operation.
Recovery
- First 2–3 days: tightness and discomfort in the chest, more so if the implant is under the muscle. Pain is controlled with the prescribed medication.
- First week: avoid raising your arms above your head and lifting. You can shower as instructed at discharge, usually after the first 1–2 days.
- After 7–10 days: most women return to desk work. You can drive again when arm movement is no longer painful and you can brake suddenly safely, usually after 1–2 weeks.
- 4–6 weeks: the support bra is worn day and night; sport and physical effort resume gradually after about 6 weeks.
- 3–6 months: the implants “drop” into their final position and the breasts take on a natural shape. The scar keeps fading for up to a year.
Results
The volume is visible straight away, but the final shape appears after a few months. Implants are not lifetime devices: many women live for decades with the same implants, but some will need another operation to replace them, for example because of capsular contracture, rupture or changes in the breast over time. Results vary from one patient to another.
Risks and things to know
- Capsular contracture: the tissue that forms around the implant can harden and distort the breast; it sometimes requires further surgery.
- Haematoma, seroma or infection: rare, but they may need additional treatment.
- Changes in sensation of the nipple or skin, usually temporary.
- Asymmetry, malposition or visible implant edges in very slim women.
- Implant rupture over time; silicone implants are checked periodically with ultrasound or MRI, as the doctor recommends.
- Breast implant-associated anaplastic large cell lymphoma (BIA-ALCL): a rare disease, linked mainly to textured implants; swelling that appears years after surgery should be checked by a doctor.
Most women with implants can breastfeed. If you have a mammogram, tell the radiographer that you have implants.